


If your child has a food allergy, you may wonder whether oral immunotherapy could help reduce the risk from accidental exposure. But having a food allergy does not automatically mean a child should start OIT.
Food allergy immunotherapy eligibility depends on several factors: whether the allergy is clearly confirmed, which food is involved, your child’s medical history, control of other allergic conditions, the likelihood of naturally outgrowing the allergy, and whether the child and family can safely commit to treatment.
The decision is therefore less about meeting one age or test-result cut-off and more about asking:
Is OIT likely to offer meaningful benefit for this particular child, and can it be carried out safely?
What Is Food Allergy Immunotherapy?
Oral immunotherapy, commonly called OIT, involves giving a person with a confirmed food allergy gradually increasing amounts of that allergen under a structured medical treatment plan. The aim is usually desensitisation. This means increasing the amount of food a child can tolerate before developing an allergic reaction.
OIT is not generally considered a cure. Children undergoing treatment may still need to avoid uncontrolled exposure, carry adrenaline when prescribed, and continue following their allergy action plan.
Current European guidance recommends peanut OIT for eligible children and adolescents with IgE-mediated peanut allergy to achieve desensitisation. OIT may also be considered for selected children with persistent milk or egg allergy, generally after the age when spontaneous resolution is more likely to have occurred.
The First Requirement: Is the Food Allergy Confirmed?
Before discussing OIT eligibility for children, the diagnosis itself needs to be clear. Oral immunotherapy is intended for children with a genuine food allergy, particularly an IgE-mediated food allergy.
An IgE-mediated reaction usually develops relatively soon after eating the food and may cause symptoms such as:
- Hives
- Swelling
- Vomiting
- Coughing
- Wheezing
- Breathing difficulty
- Anaphylaxis
The allergist will look at the child’s reaction history together with appropriate allergy testing.
This may include:
- Skin prick testing
- Food-specific IgE blood testing
- Component testing in selected situations
- Previous medical records
- Previous oral food challenge results
A positive skin or blood test alone does not prove that a child will react when the food is eaten. When the diagnosis remains uncertain, a medically supervised oral food challenge may sometimes be needed to confirm or rule out the allergy before OIT is considered.
This distinction matters because a child should not undergo months or years of food immunotherapy for an allergy they may not actually have.
Which Food Allergies May Be Considered for OIT?
Not all food allergies have the same evidence for immunotherapy.
Peanut allergy
Peanut is one of the most extensively studied foods in OIT.
Current EAACI guidance recommends peanut oral immunotherapy for eligible children and adolescents with confirmed IgE-mediated peanut allergy to increase the reaction threshold while on treatment.

Cow’s milk and egg allergy
Many young children naturally outgrow milk or egg allergy.
For that reason, the child’s age, reaction history, current level of tolerance, and likelihood of natural resolution need to be considered before immunotherapy is started.
EAACI guidance suggests OIT for selected children with persistent cow’s milk or egg allergy, generally after around four years of age.
Other food allergies
OIT has also been studied and used for other foods in specialist settings, but the quality and amount of evidence vary depending on the allergen and protocol.
The fact that OIT is technically possible for a particular food does not automatically mean it is the most appropriate option for every child.
Does Age Determine Whether a Child Is Eligible for OIT?
There is no universal age that makes every child eligible or ineligible.
Age is one factor among many.
For certain food allergies, particularly milk and egg, doctors may consider whether there is still a reasonable chance the child will naturally outgrow the allergy before recommending a long-term treatment programme.
Research has also increasingly examined OIT in younger children, including preschool-aged children, but treatment decisions still depend on the allergen, available protocol, individual child, and expertise of the treating centre.
So rather than asking:
“Is my child old enough for OIT?”
a more useful question is:
“At my child’s age and with this particular allergy, what are the advantages of starting now compared with continued observation and avoidance?”
What Does the Allergist Assess Before Recommending OIT?
OIT suitability is based on the whole child, not simply an allergy test. Several areas need to be reviewed.
1. Previous allergic reactions
The allergist will want to know:
- What food caused the reaction?
- How much was eaten?
- How quickly did symptoms develop?
- Which symptoms occurred?
- Was adrenaline required?
- Has the child reacted more than once?
- Has the reaction threshold changed over time?
These details help confirm the diagnosis and understand the child’s risk profile.
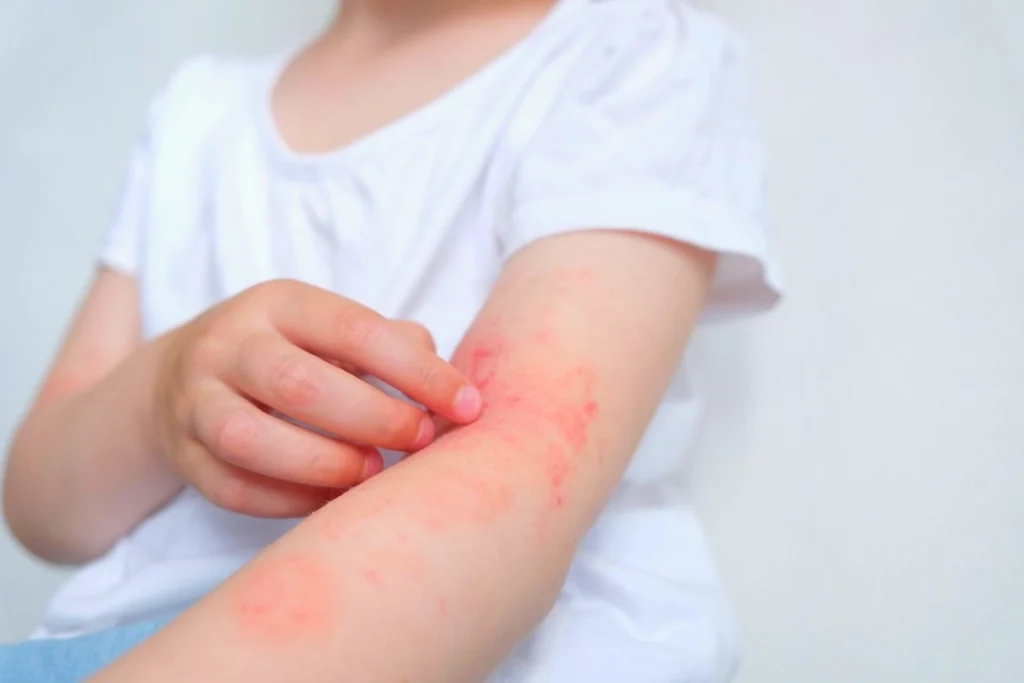
2. Asthma Control
Asthma deserves particular attention before food immunotherapy.
A child with asthma is not automatically excluded from OIT.
However, uncontrolled asthma is considered a major contraindication to starting OIT because it can increase the danger associated with allergic reactions.
Asthma should therefore be well controlled before treatment begins and monitored throughout OIT.
If a child’s asthma is currently poorly controlled, the safer approach may be to improve asthma management first and reconsider OIT later.
3. Gastrointestinal History
The allergist may ask about symptoms such as:
- Frequent abdominal pain
- Recurrent vomiting
- Difficulty swallowing
- Food getting stuck
- Pain while eating
This matters because eosinophilic oesophagitis, or EoE, is an inflammatory condition of the oesophagus associated with food allergy and can also develop or become apparent during OIT.
Active EoE is generally considered an important contraindication to OIT, although published guidelines differ somewhat in how they classify previous or inactive EoE.
If there are concerning gastrointestinal symptoms, these may need to be assessed before immunotherapy is considered.
4. Other Allergic Conditions
Children being assessed for OIT may also have:
- Eczema
- Allergic rhinitis
- Asthma
- Other food allergies
These conditions do not automatically prevent treatment.
However, significant uncontrolled allergic disease may need to be stabilised first
For example, active severe eczema can make it harder to judge whether new skin symptoms are being caused by an OIT dose and may need better control before treatment begins.
5. Likelihood of Naturally Outgrowing the Allergy
Not every childhood food allergy persists for life.
Milk and egg allergies, in particular, may resolve naturally in some children.
Some children with milk or egg allergy may also tolerate baked forms of these foods even though they react to less-heated forms.
Before beginning long-term immunotherapy, the allergist may therefore consider:
- Your child’s age
- Previous reactions
- Changes in allergy tests over time
- Whether baked forms are tolerated
- Previous oral food challenges
- The natural history of that particular food allergy
In some situations, reassessment or a supervised food challenge may be more appropriate than immediately beginning OIT.
6. What Does the Family Want OIT to Achieve?
Eligibility is not only about medical test results.
The family’s treatment goals matter.
Some parents may be primarily concerned about a severe reaction from a tiny accidental exposure.
Others may find that the allergy significantly affects:
- School
- Restaurants
- Birthday parties
- Travel
- Family meals
- Social activities
- Anxiety around food
Increasing the reaction threshold may therefore provide meaningful benefit for some families. International expert consensus has identified concerns around accidental exposure, quality of life, and the burden caused by food allergy as relevant factors when considering OIT.
But expectations need to be realistic. OIT should not be started with the assumption that the child will definitely be able to eat unlimited quantities of the allergen afterwards.
7. Can the Family Commit to the Treatment?
This is an important part of food allergy immunotherapy eligibility that can easily be overlooked.
OIT requires considerable participation from both the child and caregivers.
Depending on the treatment protocol, families may need to manage:
- Regular home doses
- Clinic visits for dose increases
- Monitoring after doses
- Restrictions around exercise or other dosing cofactors
- Adjustments during illness
- Missed-dose instructions
- Recognition of allergic reactions
- Prompt use of adrenaline when required
- Long-term maintenance dosing
Parents need to understand the treatment plan and be comfortable managing reactions if they occur.
Guidelines specifically identify adherence, willingness to use adrenaline, ability to attend appointments, and capacity to follow home-dosing instructions as important considerations when selecting patients for OIT.
If the treatment routine cannot be followed safely, OIT may not be the right option at that time.
Does a Previous Severe Reaction Mean My Child Cannot Have OIT?
Not automatically.
It may sound logical to assume that a child who has previously experienced anaphylaxis is “too allergic” for immunotherapy.
That is not necessarily the case.
A previous history of anaphylaxis to the food is not by itself considered an absolute contraindication to OIT.
However, the severity and circumstances of previous reactions are still important when assessing risk, planning treatment, and deciding how closely the child needs to be monitored.
This is another reason eligibility cannot be decided from one feature of the child’s history.
What If My Child Has More Than One Food Allergy?
Having multiple food allergies does not automatically exclude a child from OIT either. Clinical guidance recognizes that children with multiple food allergies may still be considered for treatment. However, managing several allergies can make the practical decision more complicated.

The allergist may need to discuss:
- Which allergy creates the greatest risk or burden
- Whether one or several foods should be considered
- Nutritional impact
- Treatment complexity
- Family capacity to manage the protocol
The best approach may therefore differ considerably from one child to another.
When Might OIT Not Be Appropriate?
There are situations where food allergy immunotherapy may need to be avoided, delayed, or considered only after further assessment.
Examples include:
The food allergy has not been properly confirmed
Starting immunotherapy without a reliable diagnosis can expose a child to unnecessary treatment and risk.
Asthma is uncontrolled
Asthma needs to be brought under good control before OIT is started.
Active eosinophilic oesophagitis is present
OIT may worsen or complicate eosinophilic gastrointestinal disease and generally requires a different approach.
Another medical condition increases treatment risk
Certain significant medical conditions or medications may influence whether immunotherapy can be carried out safely and require individual specialist assessment.
The child or family cannot follow the treatment plan safely
Repeatedly missing doses, being unable to attend important follow-ups, or being unwilling to use adrenaline during a significant reaction can make OIT unsafe.
The treatment burden outweighs the likely benefit
OIT requires a long-term commitment.
If continued avoidance is manageable and the expected benefit of immunotherapy is limited, a family may decide that OIT is not currently the right option.
Not being suitable today does not always mean a child will never be suitable.
Some factors, such as uncontrolled asthma or severe eczema, can potentially be treated and reassessed.
A Positive Allergy Test Does Not Automatically Make a Child an OIT Candidate
This deserves emphasis.
Parents sometimes arrive at an allergy consultation after being told:
“The test is strongly positive, so your child needs immunotherapy.”
Food allergy diagnosis is more nuanced than this.
Skin prick and blood tests indicate allergic sensitisation. They need to be interpreted alongside the child’s actual reaction history.
Depending on the situation, an allergist may determine that a child needs:
- Continued avoidance
- Repeat assessment
- A supervised oral food challenge
- Introduction of a tolerated form of the food
- OIT
- Another management approach
Choosing the correct path begins with understanding exactly what the child is allergic to and how clinically significant that allergy is.
Who May Be a Good Candidate for OIT?
Rather than using a strict checklist, a child who is being considered for OIT will often have several of the following characteristics:
- A well-confirmed IgE-mediated food allergy
- An allergy for which immunotherapy has appropriate supporting evidence
- A meaningful risk or burden from continued allergy
- Controlled asthma and other allergic conditions
- No medical condition that makes OIT unacceptably risky
- A child and family who understand the benefits and limitations
- Ability to attend treatment and follow-up appointments
- Ability to follow the home-dosing protocol reliably
- Willingness to recognise and treat allergic reactions
- Realistic expectations about what OIT can achieve
Even then, treatment is a shared decision rather than an automatic recommendation.
What Should Parents Ask Before Starting OIT?
If food allergy immunotherapy is being considered for your child, useful questions include:
- Are we certain my child still has this food allergy?
- Could my child naturally outgrow it?
- Why are you recommending OIT now?
- What is the goal in my child’s case?
- What benefit can we realistically expect?
- What reactions can occur during treatment?
- Is my child’s asthma adequately controlled?
- What happens if doses are missed?
- How much time will the treatment require?
- How long might maintenance continue?
- Will my child still need to avoid the food?
- Will we still need to carry adrenaline?
- What other options do we have if we decide against OIT?
A good OIT discussion should include the reasons for and against treatment.
Frequently Asked Questions On Candidate for Food Allergy Immunotherapy
Is every child with a food allergy eligible for OIT?
No. Eligibility depends on confirming the allergy, the food involved, medical history, other allergic conditions, treatment goals, safety considerations, and the family’s ability to follow the treatment programme.
Does my child’s allergy test need to reach a certain number before OIT?
There is no single IgE level or skin-test size that by itself determines OIT suitability. Test results need to be interpreted together with the child’s clinical history.
Can a child with asthma undergo OIT?
Potentially, yes, if the asthma is well controlled. Uncontrolled asthma is a significant contraindication and should be addressed before OIT begins.
Can a child who has previously had anaphylaxis receive OIT?
A previous episode of anaphylaxis does not automatically exclude a child from OIT. It does, however, require careful risk assessment and appropriate specialist supervision.
Can children with several food allergies have OIT?
Multiple food allergies are not automatically a contraindication. The allergist will need to determine which foods should be considered and whether the proposed programme is practical and appropriate for the child.
What if my child is not suitable for OIT right now?
OIT is only one way to manage food allergy. Continued avoidance, emergency preparedness, reassessment, supervised food challenges, dietary guidance, or other treatment approaches may be more appropriate depending on the situation.
Is Food Allergy Immunotherapy Right for Your Child?
The best candidate for food allergy immunotherapy is not simply the child with the highest allergy-test result or the most frightening previous reaction.
Suitability comes from looking at the complete picture: Is the allergy confirmed? Is OIT appropriate for this particular food and age? Are asthma and other conditions controlled? What does the family hope to gain from treatment? And can the treatment be followed safely over the long term?
For parents considering OIT, Dr. Mahesh Katre can review the child’s reaction history, allergy testing, other allergic conditions, and current food restrictions to help determine whether immunotherapy should be considered or whether another approach may make more sense.
Sometimes that discussion leads to OIT. Sometimes it leads to further testing, a supervised food challenge, continued avoidance, or simply reassessing the allergy first. The important step is choosing the approach that is appropriate for the individual child rather than assuming every food allergy needs the same treatment.


